Safer-Med

Your nurses stand at the last checkpoint. Give them a backstop.

Medication harm is a systems problem — not a people problem. When something goes wrong at the cabinet, the nurse is the last person to touch the dose, and too often the first to be blamed. Safer-Med is a real-time safety net at the dispensing cabinet: it gives the nurse a quiet heads-up when a dose has become risky for the patient, in time for a second look before it reaches them. Built to support nurses’ judgment, not add to their alert load.

Advisory, not directive · on the phone they already carry · no new charting

Why it matters for nursing

A safety layer that has your nurses’ backs.

Nurses have earned their skepticism of “safety” technology. What follows is built around that, not in spite of it — support, not surveillance.

  • Has your nurses’ backs

    A real-time backstop at the moment of highest risk — and a record that the system stood behind the nurse, not one that only scrutinizes them after the fact.

  • Designed to minimize workflow burden

    On the communication tools nurses already use — no new app, no login, no routine additional charting. It’s designed to alert only on new, clinically meaningful risk, and that alert burden is measured in shadow mode before it ever reaches the floor.

  • Respects scope of practice

    Advisory by design — it asks for a second look; the nurse always decides. Judgment is informed, never overridden by software.

  • Nurses help shape it

    It relieves the weight of being the unsupported last line — and, as a development partner, your nurses shape how the heads-up works, from wording to timing. Shared governance, not a tool handed down.


From the nurse’s chair

Two failure modes land squarely on the nurse.

Neither is about how carefully a nurse works. Both are gaps in the system around them — and both are what Safer-Med is built to catch.

The approved order that turned unsafe

The nurse did everything right — and the dose is still dangerous

A nurse gives exactly what was ordered. But a platelet count that fell overnight quietly made that anticoagulant dose newly risky, and nothing at the cabinet re-checked it. The order was safe when written and safe at pharmacy review — the patient’s picture changed after, and no one re-ran the check.

The override that doesn’t fit the patient

A wrong-drug pull, often with no patient-specific check downstream

Under time pressure, an override releases a drug before any pharmacist review — the setup for a wrong-drug pull, a paralytic instead of the sedative beside it. It isn’t about how often nurses override; most overrides are appropriate. But the small fraction that aren’t can send a wrong drug to the patient, often with no patient-specific check downstream to catch it — and even one can be fatal. The nurse is left holding it alone.

How it reaches the nurse

A quiet second look — routed to the right nurse, in time.

01 · Routed to you

To the nurse holding the dose, on the phone you already carry

The moment a pull or override doesn’t fit the patient, Safer-Med sends a heads-up — after the pull, before the medication reaches the patient — to the nurse, on the clinical-communications app your unit already uses. No new app, no new login.

02 · It asks, you decide

Advisory by design — it never blocks the cabinet

Safer-Med surfaces the finding and the reason behind it, and asks for a second look. It never locks a drawer, never delays a dispense, and never directs care. It informs the judgment you are already licensed to exercise.

03 · The catch is recorded and shared

Closes the loop back to pharmacy — recorded, not vanished

The nurse’s response — reviewed and held, or reviewed and given — closes the loop back to pharmacy and lands in an immutable audit trail, so a near-miss becomes a documented, reviewable event instead of a moment that vanishes. An unanswered high-risk heads-up escalates through the communications platform the team already uses. It’s a shared safety process, not a hand-off of responsibility to the nurse.

What actually reaches the nurse.

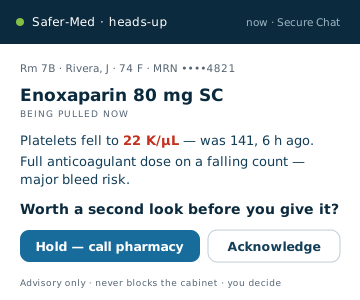
Not a dashboard, not a task list — a single heads-up a nurse can read in seconds during a med pass: who, what, what changed, why it matters now, and what to do next. Pharmacy is one tap away; the cabinet is never blocked.

Example Safer-Med heads-up on the nurse's phone: Room 7B, enoxaparin 80 mg being pulled now; platelets fell to 22 from 141 six hours ago — full anticoagulant dose on a falling count, major bleed risk. It asks "Worth a second look before you give it?" with Acknowledge and Call pharmacy options. Advisory only; never blocks the cabinet.
Illustrative — the exact fields and wording are validated with your own frontline nurses before go-live.

How it stays quiet

How it tells a wrong drug from a routine one.

On an override — a pull that skipped pharmacy review — a targeted AI check weighs that medication against the patient: does this drug fit their diagnoses, labs, and allergies, and what’s typical on the unit? So it stays quiet on the routine overrides and speaks up for the true outlier: a labor-induction drug overridden on a geriatric floor, where even a decade-experienced nurse can grab the wrong vial under pressure. Separately, personalized clinical rules re-check every dispense and override against that patient’s current labs and vitals, flagging only a dose that has turned unsafe since pharmacy last reviewed the order.

The override check weighs the medication against the patient and what’s typical on the unit — never the nurse. And a heads-up firing isn’t proof of safety: Safer-Med is measured on preventable harm caught before it reaches the patient, not on alerts sent — and both alert types are measured in shadow mode before nurses receive a single live notification.

Straight answers for nurses

The questions nurses actually ask.

We know “safety” tech has a track record with nurses: more clicks, more alerts, more second-guessing. That skepticism is earned. Straight answers:

Is this just one more alert?

No new app or login — it reaches the phone you already carry, and only when something has genuinely changed for your patient or a pull looks wrong for them. It runs in shadow mode first, and your leaders see the measured alert burden before it ever reaches the floor.

Will it slow me down?

No new charting, and the acknowledgment is one tap — most heads-ups are a quick read. When a finding does need a closer look — a clinical judgment, a quick word with pharmacy, or holding the dose — the workflow and escalation are ones nursing and pharmacy leadership agree on before go-live.

Can it lock the cabinet or stop me giving a med?

No. It never blocks or delays a dispense and never controls the cabinet. It informs — it asks, you decide.

What if I look and I’m right to give it?

Expected — you know your patient. It’s a second look, not a command. Proceeding after a heads-up isn’t a mark against you; it’s your clinical judgment, which the tool is there to inform, not replace.


Development partners

Nursing has to lead this — alongside pharmacy.

We’re seeking one or two health-system development partners, with nursing and pharmacy shaping the evaluation together. As a development partner, your nurse leaders and frontline nurses shape how the heads-up works — what it says, when it fires, how it reaches them — so it fits the way nurses actually work. It closes the loop between the nurse at the cabinet and the pharmacist who never saw the override: one safety layer, both disciplines, no new turf.

The first step is low-risk and concrete: a retrospective on your historical data, under BAA — we show your nursing and medication-safety leaders what Safer-Med would have surfaced for your nurses over the prior year, before a single live alert reaches the floor.

If your organization wants to lead in patient-safety innovation — and give its nurses a backstop they helped design — let’s talk.

The first step is a joint nursing & pharmacy workshop to scope a retrospective on your own data — it sets scope, responsibilities and decision criteria, with no commitment to later phases.

Leading pharmacy, not nursing? The same safety net speaks to override governance, Joint Commission anticoagulant safety, and pharmacist time. See the view for pharmacy leadership →

Start a conversation.

Tell us about your units and your nursing-safety priorities — we’ll show you what Safer-Med would surface for your nurses.